


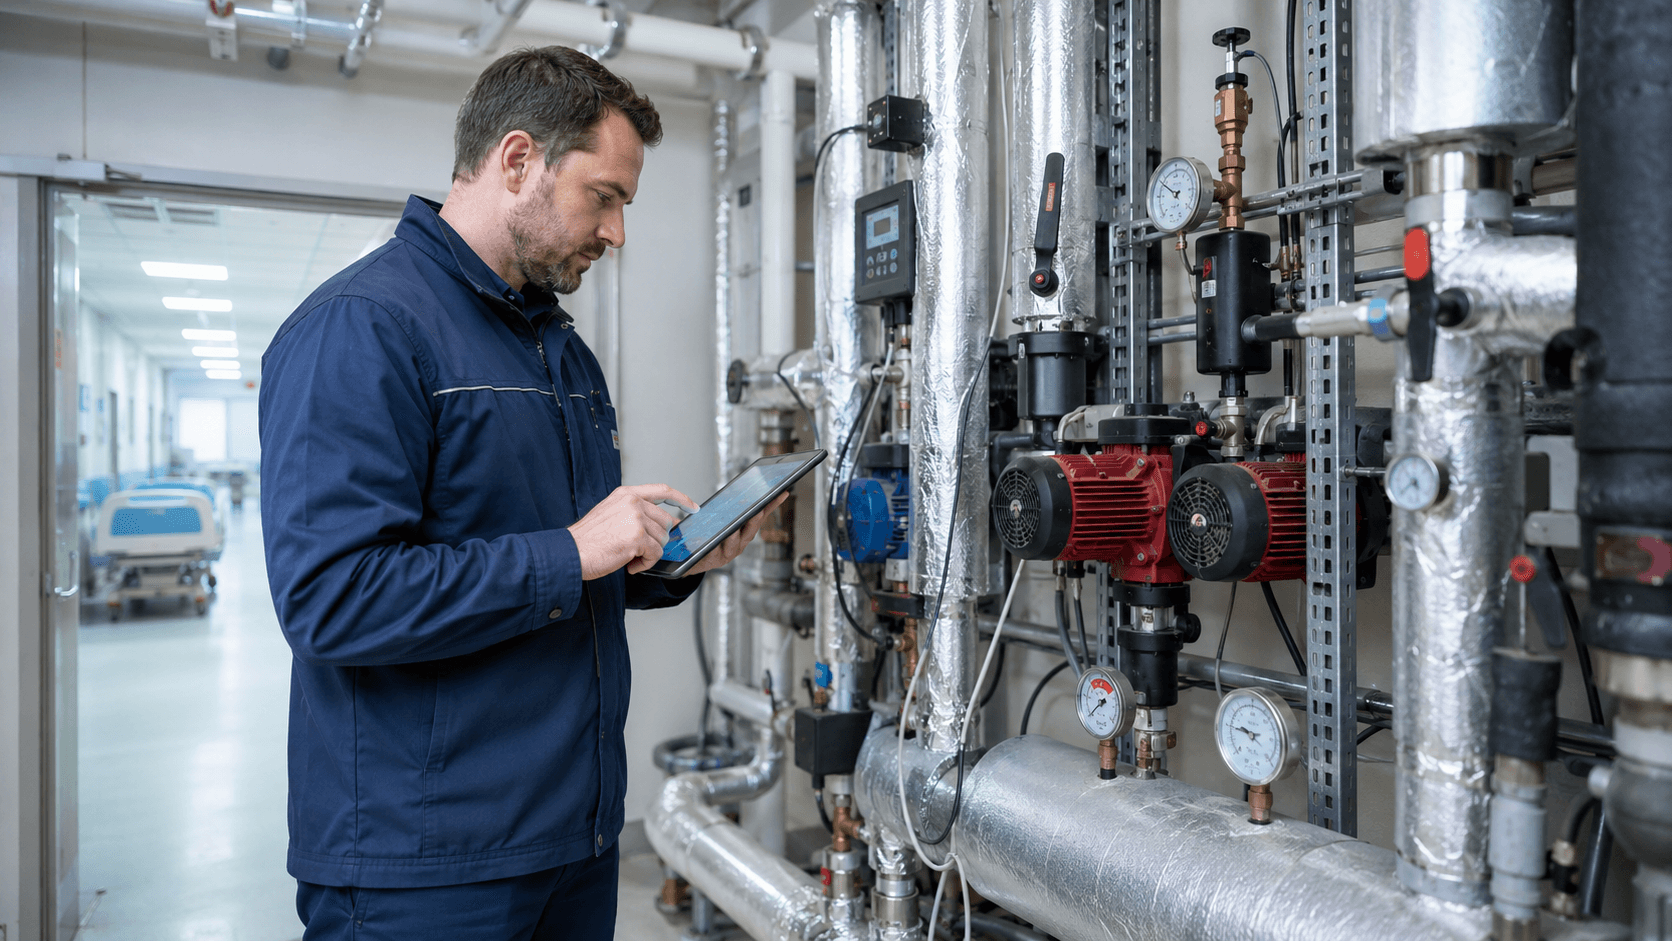
A hospital is one of the more challenging types of buildings to analyse from an energy perspective. Not because it always uses more energy than every other facility, but because many of its systems operate around the clock, individual zones have very different requirements, and upgrades must not disrupt continuity of care.
A good hospital energy audit should therefore go far beyond checking walls, windows and the heat source. It requires a heat and electricity balance, separate profiles for different parts of the facility, and an analysis of ventilation, cooling, domestic hot water, controls and metering data before upgrade options are developed.
Defining the scope boundary is equally important. A hospital building energy audit primarily concerns energy associated with the building and its systems. It does not automatically mean auditing every item of medical equipment, steriliser, laboratory device or the hospital’s entire clinical activity.
Hospital energy audit – key conclusions
- the facility should be analysed by zone and according to actual operating hours, rather than using one averaged schedule;
- the energy balance should separate building-related energy use from process loads, even if both are billed through the same meter;
- ventilation and air-conditioning require particular care because air parameters in some rooms are determined by their clinical function and sanitary requirements;
- heat recovery, airflow reductions or setpoint changes should not be proposed without checking hygiene risks and the requirements of the relevant zone;
- metering data, BMS data and consumption profiles are particularly valuable in a hospital because they help distinguish constant 24/7 base load from schedule-dependent consumption;
- an upgrade option should account not only for energy savings and cost, but also for operational continuity, phasing of works, required redundancy and the possibility of temporary shutdowns.
Why should a hospital be analysed differently from a typical office building?
In a typical office building, a significant share of systems can be linked to occupants’ working hours. That model usually does not work in a hospital. Inpatient wards, the emergency department, some diagnostic areas, technical rooms and critical systems may require continuous operation, while outpatient clinics, administration, rehabilitation and parts of the support facilities follow separate schedules.
This means that a single “hospital building” profile often does not exist. The auditor should first identify functional zones, their operating hours and required parameters, and only then allocate energy use to them. Otherwise, it is easy to classify legitimate round-the-clock equipment operation as a loss or, conversely, to overlook a system running unnecessarily throughout the night.
A hospital’s energy performance should not be assessed using a single averaged indicator. A further complication is that, in some hospitals, the same sources and systems serve both building and process needs. For example, one source may supply space heating, domestic hot water and process loads, while one electricity meter may cover air handling units, chillers and medical equipment. The utility bill alone therefore does not show where the actual savings potential lies.
First define the boundary: a building audit or the facility’s total energy use?
Under Polish regulations, a formal building energy audit includes a technical and construction inventory, an assessment of the building envelope, heating, domestic hot water, the heat source and ventilation, as well as electrical system elements where they are relevant to a thermal modernisation project. If the investor expects a broader balance covering electricity, cooling, BMS, lighting or renewable energy, this should be stated explicitly at the start of the assignment.
This is particularly important in a hospital because some loads are process-related. Their consumption may be significant in the overall balance, but that does not automatically mean that a building audit should assess the efficiency of every medical device.
| Area | Within a hospital building audit | When the scope needs to be extended |
|---|---|---|
| Building envelope, windows and doors, heating, domestic hot water, ventilation | Core area of the building analysis | When specialist measurements or process design are required |
| Air handling units, pumps, fans, building cooling, BMS | Worth analysing where they affect consumption and the planned upgrade | When detailed diagnostics of controls, hydraulics or air quality are required |
| General and technical building lighting | May be included in an extended analysis | When photometric measurements or specialist lighting design are required |
| Medical equipment, diagnostic imaging, laboratories, sterilisation, kitchen, laundry | Consumption should be separated in the balance if it affects the main meter | Assessing process efficiency requires an explicit extension beyond a standard building audit |
| Medical gas, medical compressed air and vacuum systems | May affect the facility’s energy balance | Process optimisation should be defined as a separate scope and must not compromise medical requirements |
The key principle is that even if a load is not intended or cannot be upgraded, it is still worth knowing how much energy it uses. Otherwise, process consumption can easily be attributed to space heating, ventilation or building cooling, resulting in an incorrect baseline.
What data should be prepared for a hospital building energy audit?
The more complex the facility, the more valuable actual operating data become. In a hospital, annual utility bills alone are usually not enough to understand the operating profile. Where available, it is worth compiling data from more than one full season and, for electricity, hourly or 15-minute profiles as well. This is a practical recommendation for assessing operational variability, not a universal formal requirement for every audit.
| Data | What is worth preparing | Why it is needed |
|---|---|---|
| Building documentation | floor plans, sections, envelope schedules, designs and surveys | to reconstruct geometry, zones and building-envelope parameters |
| Systems documentation | diagrams of the district-heating substation/boiler room, heating, domestic hot water, ventilation, cooling, BMS and electrical systems | to understand how energy is generated, distributed and controlled |
| Invoices and settlements | electricity, district heat, gas, fuels, cooling – where purchased | for the energy balance, cost analysis and model validation |
| Metering profiles | 15-minute or hourly energy consumption, demand profiles, heat-meter and submeter data | to identify base load, peaks and schedules |
| BMS / controls | trends for temperatures, flows, pressures, operating states, fan speeds, valve positions and AHU modes | to verify how systems actually operate, rather than how they were designed to operate |
| Zone schedules | 24/7 wards, outpatient clinics, administration, operating theatres, diagnostics, rehabilitation, kitchen and other zones | to assign the correct usage profiles |
| Upgrades and failures | window replacement, insulation works, changes to AHUs, heat sources, chillers, setpoints and controls | to explain changes in consumption over time |
| Organisational data | planned refurbishments, shutdown constraints, operational-continuity requirements | to reject options that are not practically feasible |
If some documentation is outdated, this should be established before calculations begin. In older hospitals, systems are often modified repeatedly and design drawings may no longer reflect actual conditions. In such cases, the site visit and controls data become more important than the formal equipment description.
How do you build a reliable hospital energy balance?
The first purpose of the balance is not yet to identify upgrades. Hospital energy use must first be broken down by function and profile: where, when and for what purpose energy is consumed. The balance should separate at least heat, electricity and, where applicable, cooling supplied from an external source.
Thermal energy
The heat balance should distinguish space heating, domestic hot water production and other loads supplied from the same source. If the substation or boiler room also serves process loads, their share should be identified or estimated from measurements and documented assumptions. For space heating, differences in weather conditions between seasons should also be taken into account so that mild and severe winters are not treated as directly comparable.
Electricity
For electricity, the daily load profile is particularly useful. It shows how much demand remains at night, how load changes on working days and weekends, and whether clear peaks occur. In a hospital, a high base load does not necessarily indicate inefficiency because some systems must operate continuously, but it is a starting point for separating individual loads.
A good practice is to compare the main meter with submeters and BMS trends. If the whole facility maintains high demand at night, that figure alone says little. The auditor should determine how much is attributable to ventilation, cooling, pumps, server rooms, lighting, medical equipment and other loads.
What does a hospital site visit involve?
The site visit should be planned jointly with the technical department. In a facility operating 24/7, not all rooms are accessible at any time, and some systems can only be inspected without disrupting ward operations.
The auditor should verify in particular:
- the condition of external walls, roofs, floors/ceilings, windows and doors, including visible air leakage or thermal bridges;
- heat substations, boiler rooms, backup heat sources and the heat distribution system;
- pumps, heat exchangers, headers, pipe insulation and the method of heating-system control;
- domestic hot water production, circulation, storage tanks, heat exchangers and system insulation;
- air handling units: filters, heat exchangers, heat recovery, heaters, cooling coils, fans, variable-frequency drives and controls;
- chillers, cooling towers or dry coolers, circulation pumps, hydraulic separators and chilled-water parameters;
- BMS and local controllers – not only the graphical interface but also available trends and alarm history;
- lighting in general, technical and selected clinical areas within the scope adopted for the audit;
- existing renewable energy systems and technical conditions for new installations;
- meters and submeters, and locations where the lack of metering prevents key loads from being separated.
If the data are inconsistent, the site visit can be extended to spot measurements of power, temperatures, flows, ventilation parameters or pump and fan operation. The measurement scope should follow a specific hypothesis. Simply having a meter is not a reason to perform every possible measurement.
Which systems require particular attention in a hospital?
Building envelope and windows/doors
Walls, the roof, floors/ceilings, windows and doors remain an important part of the audit, but their share of the savings potential should be assessed together with system operating profiles. Insulation can reduce heat demand and heating capacity, but it will not solve the problem of air handling units operating at incorrect airflow or domestic hot water losses. Window replacement also requires checking its impact on room ventilation.
Heat source and heating system
The audit should assess source efficiency, supply and return temperatures, control strategy, hydraulic balancing, pump operation and whether the source matches the current load. Selecting a new source before calculating the effect of thermal modernisation can lead to oversizing.
If one source serves several buildings or both building and process needs, a load balance should be developed first. Only then is it possible to determine whether the priority is to upgrade the source, internal network, controls, or whether part of the problem lies on the demand side.
Domestic hot water
In hospitals, domestic hot water can have a high and distributed demand profile, while circulation often operates around the clock. The analysis should cover water-heating arrangements, temperatures, circulation, distribution losses, pipe insulation and storage tanks. Savings must not, however, be based on arbitrarily reducing parameters where this would compromise hygiene requirements or safe system operation.
Ventilation and air handling units
This is one of the most important areas in a hospital. The analysis should cover not only fan power but also airflows, pressure rise, filter operation, pressure drops, temperature setpoints, heating and cooling coils, AHU operating modes and schedules.
It is particularly important to distinguish AHUs serving critical zones from those that can be time-controlled. In an outpatient clinic operating during the day, continuous AHU operation may warrant investigation. In an operating theatre or isolation room, reaching the same conclusion without checking room requirements would be a mistake.
Heat recovery
Large airflows mean that heat recovery can be an important area of analysis, but ventilation systems in a hospital must not all be treated in the same way. The room function, risk of contaminant transfer, method of separating air streams and permissibility of recirculation all need to be checked.
Polish technical requirements restrict recirculation where there is a risk of pathogenic bacteria or other harmful contaminants, and in a healthcare building recirculation may be used only with the approval and under the conditions specified by the competent State Sanitary Inspector. For some systems, heat recovery with complete separation of the air streams, for example via a run-around coil system, may therefore be more appropriate than a solution based on mixing air.
Cooling and air-conditioning
In a hospital, cooling may be required not only in summer. Some technical or diagnostic rooms, or spaces with high internal gains, may require heat removal throughout the year. The audit should assess the actual cooling profile, chilled-water temperatures, chiller part-load operation, pumps, dry coolers or cooling towers, setpoints and interaction with air handling units.
Simultaneous heating and cooling requires particular attention. It may sometimes result from incorrect controls, but in other cases it is part of a dehumidification and reheating process needed to maintain the required parameters. It should not be classified as a loss without checking the function of the relevant AHU and room.
Controls and BMS
The BMS can be one of the most valuable data sources, but simply having one does not mean the systems operate optimally. Trends, schedules, setpoints, valve positions, fan speeds, alarms and operating sequences should be analysed.
A typical issue to investigate is a schedule configured years ago that no longer reflects current use. Another is a manual controls override that was intended to be temporary but became permanent. The audit should distinguish such cases from deliberate settings driven by safety and clinical requirements.
Lighting
The audit can analyse installed power, operating hours, controls and luminaire replacement opportunities, but general lighting should be separated from specialist and emergency lighting. In clinical rooms, functional requirements take precedence over the simple goal of “reducing power”.
Renewable energy
Photovoltaics can be attractive for a facility with high year-round electricity use because a substantial base load may support high self-consumption. PV capacity should not, however, be sized solely to annual consumption. The load profile, available area, grid-connection conditions and expected changes in demand after upgrades must also be considered.
A heat pump, battery storage or other solutions should likewise follow from the balance and assessed options rather than from an assumption that a given technology must be included in the project. Renewable energy systems also do not replace requirements for a backup electrical energy source and an appropriate level of uninterrupted power supply for a hospital.
Medical-room parameters are a design constraint, not an area for arbitrary savings
Polish regulations governing healthcare providers require rooms and systems to be suited to the type of activity and scope of healthcare services. Operating suites, isolation rooms and rooms for immunocompromised patients must use supply-and-extract ventilation or air-conditioning that provides air-quality parameters appropriate to the function of the room. In operating theatres and other rooms where nitrous oxide is used for anaesthesia, the regulations also specify the arrangement of supply and extract air and require positive pressure relative to the corridor.
The practical implication for an audit is important: strategies used in office buildings must not be transferred mechanically to clinical zones. Reducing airflow, changing pressure relationships, shutting down an AHU, recirculating air or changing temperature must first be assessed against the room function and applicable requirements.
An energy audit does not replace systems design or sanitary approvals. It should, however, identify which ideas can proceed to further design, which require additional analysis and which should already be rejected at the audit stage.
How are hospital upgrade options developed?
Hospital thermal modernisation should not start with a list of unrelated items of equipment to purchase. Upgrading one system changes the operating conditions of others. Improving the building envelope affects heating capacity demand, AHU upgrades change heat and electricity use, and better controls can change the future load profile before renewable energy systems are sized.
A sound sequence for the audit work is:
- define the baseline and energy-balance boundaries;
- identify possible measures for the building envelope and systems;
- reject measures that conflict with room requirements or are unrealistic in terms of operational continuity;
- calculate the energy effect of individual measures;
- build packages of measures that account for their interactions;
- compare cost, energy savings, operating costs and implementation constraints;
- identify the recommended option for the investor’s objective or financing requirements.
Under Polish regulations, a formal thermal-modernisation audit uses a prescribed optimisation methodology and, among other indicators, the simple payback period for the specified improvements. In a hospital, it is worth showing in parallel the constraints that an economic indicator alone does not capture: the ability to shut down systems, redundancy, work scheduling, required parameters and the impact on ward operations.
The least-cost energy option is not necessarily an option that can be implemented in an operating hospital. The audit should identify that difference before the design and procurement stages.
Example: an AHU operates 24/7 – does that automatically mean wasted energy?
Assume a hospital complex has two AHUs. The first serves a ward that operates around the clock. The second serves outpatient clinics open from morning until late afternoon, but BMS data show that both AHUs run continuously.
It would be wrong to conclude automatically that both systems should be switched off at night. The auditor should first map the AHUs to the zones they serve, check hygiene and process requirements, verify the outpatient-clinic schedule and determine whether contaminant sources or other ventilation needs remain at night. Only then can an option to reduce airflow or shut down the second AHU outside occupied hours be calculated.
The same principle applies to cooling, pumps, lighting and circulation: first understand the function and requirements, then optimise operating time.
Why must operational continuity be part of an upgrade audit?
A hospital cannot be treated like a facility that can simply close for several weeks while works are carried out. Even a very strong energy-saving option may prove unusable if implementation requires a prolonged interruption of heat, cooling, ventilation or power to a critical part of the building.
That is why the audit should identify, already at this stage:
- which systems can be shut down and within what time windows;
- which systems require maintained redundancy or a temporary solution;
- whether the upgrade needs to be phased building by building, floor by floor or AHU by AHU;
- whether works should be coordinated with other planned refurbishments;
- which measures require prior design documentation, sanitary approvals or additional technical analysis;
- whether option costs should include temporary systems, night work, additional safeguards or parallel operation of the old and new systems during a transition period.
The audit does not need to design the detailed organisation of works. It should, however, identify constraints that materially change the cost or feasibility of an option.
How can a hospital audit support preparation for funding?
An audit can organise the existing-state information, define the investment scope and quantify the effects of different options, which is why it is often one of the most important input documents for preparing a project financed from external funds. It should not be assumed, however, that every audit prepared earlier will automatically meet the requirements of a specific funding programme.
If a hospital audit is to support a funding application in Poland, the current call documentation should be checked before work begins: the required audit scope, energy indicators, calculation method for the effect, cost eligibility, renewable-energy requirements and any additional attachments. These conditions change over time and therefore should not be hard-coded into an evergreen article about hospital audits.
The audit itself does not guarantee that funding will be awarded. It is a tool for preparing and substantiating the investment; the outcome of the call also depends on programme criteria, completeness of documentation and project assessment.
How should a hospital prepare for an energy audit?
- Appoint a person from the technical department who knows the history of the systems and will be available during the site visit.
- Prepare a list of buildings, zones and main functions – especially those operating 24/7 and those with restricted hours.
- Collect building and systems documentation, but flag drawings and designs that no longer reflect actual conditions.
- Prepare available invoices and consumption data; if data from more than one full season are available, compile them together. For electricity, also include 15-minute or hourly profiles where available.
- Export BMS trends and schedules for the most important AHUs, sources, pumps and cooling systems.
- List upgrades completed in recent years and planned investments so that the audit does not recommend works that are already scheduled or conflict with another project.
- Describe constraints on shutdowns, room access and the need to maintain operational continuity.
- Define at the outset whether the analysis covers only the building or also specified process loads.
What should a good hospital energy audit deliver?
A good audit should enable hospital management, local-government bodies and the technical department to answer not only “what can we replace?”, but above all “where are we actually using energy, which measures are technically permissible, and which option is worth developing further?”.
At a minimum, the result should include:
- a clearly defined analysis boundary and a list of energy carriers;
- a description of the existing building and systems;
- an energy balance with the best practicable separation of major loads;
- a description of zones and usage profiles, including loads operating 24/7;
- a list of problems and potential upgrade measures;
- upgrade options with their energy and economic effects;
- identification of medical, sanitary and operational constraints affecting the options;
- information on which measures require further design, measurements or approvals;
- material that can be used when preparing the design, procurement procedure or financing documentation.
In practice, one of the greatest benefits of an audit is often organising the relationships between the building, its systems and the way it is used. In a hospital, those relationships determine whether a solution that looks energy-efficient on paper can actually be implemented safely.
Frequently asked questions
Does a hospital operating 24/7 always have little potential for time-based control?
No. Round-the-clock operation of the facility does not mean that every zone and every device must run at full output for 24 hours. Critical areas should be separated from outpatient clinics, administration and other zones with limited schedules, and the requirements of the specific system should be checked.
Does a hospital energy audit include medical equipment?
Not automatically. Medical equipment may account for a significant share of consumption and is therefore worth separating in the energy balance, but an assessment of its process efficiency should be explicitly included in the scope if it is to form part of the assignment.
Does heat recovery from ventilation always make sense in a hospital?
No. The potential may be significant, but the solution depends on room use, the ability to separate air streams, hygiene requirements, temperatures, operating hours and economics. In some systems, sanitary constraints will determine the technology choice or rule out specific solutions.
Should replacing the heat source be the first measure?
There is no such rule. It is better to calculate demand after changes to the building envelope, ventilation, controls and other systems. Otherwise, the new source may be sized for conditions that no longer exist after the upgrade.
Is a hospital building audit the same as the mandatory enterprise energy audit in Poland?
No. These are separate types of assessments with different legal bases, boundaries and purposes. A building audit focuses on the facility and its upgrade; it should not automatically be treated as fulfilling the Polish obligation to carry out an enterprise energy audit.
Legal and technical basis
In Poland, the scope of a formal building energy audit is defined by the Regulation of the Minister of Infrastructure of 17 March 2009 on the detailed scope and form of energy audits and the algorithm for assessing the cost-effectiveness of thermal-modernisation projects, as subsequently amended.
Requirements for rooms and equipment used by healthcare providers in Poland derive, among other provisions, from the Regulation of the Minister of Health of 26 March 2019; its consolidated text was published in the Polish Journal of Laws of 2022, item 402. For ventilation and heat recovery, the Polish technical requirements for buildings and their location are also relevant.
For a specific project, the requirements arising from room function, process documentation, applicable standards and approvals relevant to the scope of the upgrade must also be taken into account.
Summary
A hospital energy audit should start with the energy-balance boundary and actual data, not with a ready-made list of technologies. Only after separating zones, 24/7 profiles, building needs and process loads is it possible to assess the building envelope, heat sources, domestic hot water, ventilation, cooling, BMS, lighting and renewable energy reliably.
The priority is to preserve the parameters required for clinical rooms and continuity of facility operations. An option that cannot be implemented safely in an operating hospital is not a good option simply because it offers an attractive payback period.
If a hospital is preparing a thermal-modernisation project, it is worth starting by organising documentation, metering data and operational constraints. The audit can then provide the technical and economic basis for design, financing and further investment decisions.



